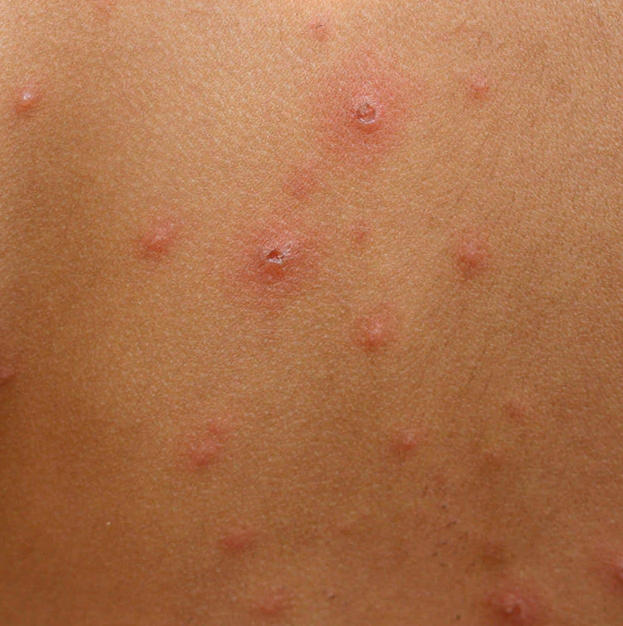
Hand, foot and mouth disease is the childhood illness that closes a preschool corner. It is endemic in Singapore, it has no vaccine here, and most children still do not need a children's emergency department to have it named.
The Communicable Diseases Agency's HFMD page, updated 7 November 2025, is the source for the rules below. A GP or a polyclinic can diagnose the usual case. The emergency visit is for the child who will not drink, will not wake, or cannot breathe comfortably.
What HFMD looks like
HFMD is an enterovirus infection. It is most common under 5, and it spreads in childcare and preschool because children share toys, hands, and bathrooms. Adults can catch it. The serious risk sits with young children.
The usual picture is a fever, mouth ulcers, a sore throat, a poor appetite, and a rash or blisters on the hands and feet. The buttocks are a common place for the rash as well. One infection protects against that strain only. A different enterovirus can do it again.
The incubation period is typically 3 to 5 days, and can run from 2 to 14. A child can be infectious before the rash is obvious. Transmission is faecal-oral, and also by saliva, respiratory droplets, and fluid from the blisters. Washing hands after the toilet and before food is the useful habit. Sharing a spoon is not.
There is no approved HFMD vaccine in Singapore, and no drug that clears the virus. Care is fluids, pain relief for the ulcers, and watching the child. Rare complications include dehydration, meningitis, encephalitis, and paralysis. Nail loss can follow. Those are reasons to know the warning signs, not reasons to sit in an emergency waiting room for a mild rash.
| What you see | What to do |
|---|---|
| Fever, mouth ulcers, and a rash or blisters on the hands, feet, or buttocks, and the child is still drinking | A GP or a polyclinic. Tell the preschool or childcare centre the same day. |
| Not drinking, vomiting that will not stop, no urine for 6 to 8 hours, hard to wake, a seizure, fast breathing, pale or blue skin, or a stiff neck | A children's emergency department, or 995. Do not wait for a clinic appointment. |
| The rash is improving and you are asking when school starts again | Stay home until the blisters have dried, the child has recovered, or the medical certificate has expired. The centre should not take them back earlier. |
SingHealth says the same split in plain language: a family doctor or a polyclinic can confirm ordinary HFMD. Do not rush to children's emergency only for the diagnosis. Go there if the child cannot swallow, vomits and will not stop, looks dehydrated, is drowsy or disoriented, has a seizure, is breathing hard, turns pale or blue, or has a sudden headache with a stiff neck. NUH adds a practical hydration check: no urine for 6 to 8 hours.
Tell the preschool or childcare centre the day you suspect HFMD. The child stays home until the blisters have dried, they have recovered, or the medical certificate runs out. Whichever of those the doctor used is the return date.
A fever of 38°C with mouth pain is a reason to look at the hands and feet, not only to give paracetamol. If the ulcers stop the child drinking, the fever medicine is not the visit. The visit is.
Colds, and the illnesses people mix up with HFMD
A cold is still the illness children get most often. Runny nose, cough, sneeze, sometimes a fever, no blisters on the palms. Rest and fluids are the treatment. A cold that becomes fast breathing is no longer a cold you watch at home. The GP versus A&E list is the line for that.
Ear infections show up as night waking, irritability, and a toddler pulling at an ear. The tubes in young children are short, so fluid sits and infects. Some settle without antibiotics. A high fever or pain that is still there the next day is a GP or paediatric visit, not a second night of guessing.
Gastroenteritis is vomiting and diarrhoea, with or without fever. The job is drinks, little and often. Continuous vomiting, or blood, belongs in the emergency row. A child who is keeping sips down can be seen at a clinic.
Chickenpox is less common than it was because varicella is on the national childhood schedule, as a separate injection at 12 months and as MMRV at 15 months. An itchy crop of blisters plus fever can still be chickenpox in a child who missed those doses. HFMD blisters cluster on the hands, feet, and mouth. Chickenpox spreads across the trunk. If you cannot tell them apart, that is what the GP appointment is for. Do not send either child to preschool to "see if it spreads."
Asthma is a longer condition, not a week-long bug. Cough, wheeze, and breathlessness need the plan the child's doctor already wrote. A first wheeze, or breathing that does not ease, is an urgent visit. Dust and colds set it off. They do not replace the inhaler plan.
What actually cuts the next bout
Handwashing, not sharing cups, and keeping a sick child home are the measures CDA names. At home, wash hands after nappy changes and wipe toys and surfaces the sick child has used. The virus also leaves in stool, so the bathroom clean matters after the rash has faded. Schools are asked to clean shared items during an outbreak and to send unwell staff home as well as children. There is no HFMD shot to book. The shots that do exist, measles and the rest of the schedule, prevent different illnesses. A child who is home with HFMD is not a reason to skip the vaccine visit that is already due once they have recovered.
Sleep and ordinary food matter for the week they are sick. They do not replace exclusion from childcare. A centre that asks for a clearance letter is following the "blisters dried or MC expired" rule. Ask the clinic for that letter at the recovery check if the centre requires one. Do not invent an earlier return because the fever stopped on day two while the blisters are still wet.
FAQ
Does every HFMD rash need a children's emergency department?
No. If the child is alert and drinking, start with a GP or a polyclinic. Emergency care is for dehydration, a change in behaviour, a seizure, or trouble breathing.
Can my child get HFMD twice?
Yes. Immunity is to the strain they just had. Another enterovirus can cause it again.
When can they go back to school?
When the blisters have dried, they have recovered, or the MC has expired. Tell the school as soon as you know. CDA asks centres to send unwell children home and to watch the others.
Is a cough and a fever HFMD?
Not by themselves. Look for mouth ulcers and a rash on the hands, feet, or buttocks. A cough and fever without that rash is much more often a cold. Either way, a child who stops drinking needs a doctor.
Book the GP or polyclinic for a child who looks like the top row of the table. Use a paediatric clinic if that is who already knows your child. If they have stopped drinking or you cannot wake them properly, skip the booking and go to children's emergency.